


Showing items3 of 6
Choose a revenue cycle partner that protects patients financially
The right revenue cycle partner protects the patient financial journey. | Start With Affordability
Healthcare providers should evaluate a revenue cycle management partner by asking a patient-centered question: Can this organization prevent avoidable financial harm while improving operational and financial performance? The answer requires more than promises about collections, automation, or staffing. A qualified partner should demonstrate how it establishes accurate coverage, estimates responsibility, prevents billing defects, connects patients with assistance, and resolves exceptions before uncertainty becomes a corrected statement or unaffordable balance.
The stakes are significant. A 2024 KFF analysis estimated that Americans owe at least $220 billion in medical debt; approximately 14 million adults owe more than $1,000. Meanwhile, a 2024 American Hospital Association report found that administrative costs represented more than 40% of hospital expenses, while commercial and Medicare Advantage care denials rose 20.2% and 55.7%, respectively, between 2022 and 2023. Partner selection therefore affects both institutional resilience and the patient experience.
Ten evaluation criteria reveal whether an RCM partner is patient-centered. | Evaluate Ten Capabilities
1. Coverage accuracy should come before collections. Patient access management, eligibility and benefits verification and insurance discovery should prevent avoidable self-pay classification and responsibility errors. Ask for eligibility accuracy, coverage-found rates, and related denials.
2. Authorization should protect access to care. Prior authorization workflows should identify requirements early, track payer decisions, escalate delays, and measure authorization-related denials and rescheduling.
3. Estimates should be explainable and reliable. Price transparency and patient estimates should combine known services, contracted rates, current benefits, and documented assumptions. Require estimate accuracy and variance reporting.
4. Affordability pathways should be built into clearance. Financial clearance and counseling should connect eligible patients with assistance, Medicaid screening, charity care, and suitable payment options before balances age.
5. Billing accuracy should be prevented upstream. Clinical documentation integrity, medical coding, and revenue integrity should reduce unsupported, missing, or duplicate charges. Ask how defects are intercepted before claims and statements.
6. Claims should be validated before submission. Claims editing and clean-claim validation should improve first-pass acceptance, while payment posting and reconciliation should allocate payer and patient responsibility correctly.
7. Patient communication should make action easier. Patient communication should be timely, plain-language, accessible, and consistent with HFMA’s 2024 Patient Financial Communications Best Practices, which connect a good financial experience with lower administrative cost, stronger results, and better patient decisions.
8. Technology should connect work, not fragment it. Revenue cycle execution systems and EHR integrations should connect EHR, payer, clearinghouse, workflow, and reporting data. Test exception visibility, data lineage, security, and human oversight.
9. Governance should expose causes and ownership. Open Accountability should define who owns an exception, when it escalates, and how learning returns upstream. A partner should show root-cause trends, corrective actions, and sustained results rather than activity counts.
10. Outcomes should unite patient and provider value. First-Pass Performance should reduce repeat touches and corrected bills while elevating patient experience, reducing cost to collect and accelerating cash.
A buyer scorecard turns promises into comparable evidence. | Score Operating Evidence
A credible evaluation tests evidence, governance, and fit. | Test Accountability
Ask partners to demonstrate three real workflows: an authorization exception, a changed estimate, and a denied claim transferred toward patient responsibility. Require each partner to show the data used, decision path, escalation, communication, correction, and root-cause feedback. Then validate reference-client results by care setting, payer mix, EHR, scope, and operating model. For example, this outsourced coding transition case study illustrates why disciplined transition governance and quality control matter when continuity and cash are at risk.
Score partners on measurable baselines and improvement commitments, not generic maturity claims. Useful measures include estimate accuracy, coverage discovery, authorization turnaround, eligibility and authorization denials, pre-bill interception, clean-claim rate, corrected statements, avoidable patient-balance transfers, inquiry resolution, financial-assistance screening, and cost to collect. Contract language should define data access, reporting cadence, escalation thresholds, patient communication standards, transition milestones, and ownership for corrective action.
Before contracting, examine how the partner will operate across each care setting. Enterprise health systems, ambulatory surgery centers, and physician practices and groups have different scheduling patterns, payer rules, coding complexity, patient-responsibility profiles, and integration constraints. Confirm that staffing, quality sampling, business-continuity planning, and governance reflect those differences. A strong partner should also explain which decisions remain with the provider, which are delegated, and how policy changes are translated into frontline workflows without disrupting patients.
The best partner does not promise to make every balance affordable. It helps the provider make every financial interaction more accurate, understandable, timely, and accountable. That operating discipline reduces rework, protects patient trust, and gives leaders a clearer path to transform revenue cycle performance without separating financial outcomes from the experience of the people receiving care.

Ten revenue cycle controls that protect patients before the bill arrives
Patient affordability begins long before a statement is mailed. | Why Controls Matter
The patient affordability-centered revenue cycle is the set of operational controls that protects patients from avoidable financial harm across scheduling, registration, coverage, authorization, documentation, coding, claims, and billing. It does not change the clinical price of care or the patient’s benefit design. It does improve whether the right account, coverage, responsibility, estimate, and assistance pathway are established before an inaccurate or unexpected balance reaches the patient.
The need is material. A 2024 KFF analysis estimated that Americans owe at least $220 billion in medical debt; about 14 million adults owe more than $1,000. A separate 2024 KFF explanation of surprise bills noted that billing or plan-processing mistakes can still cause patients to be charged more than they should owe. These findings make accuracy, clarity, and timely resolution patient-protection priorities.
Ten controls can prevent financial harm before the bill. | Ten Preventive Controls
1. Match the patient to the correct record. Registration quality should validate identity and demographics at entry. AHIMA reported in 2024 that 45% of large hospitals had difficulty accurately identifying patients through electronic health information.
2. Verify coverage and benefits early. Eligibility and benefits verification should confirm active coverage, benefit limits, deductibles, coordination of benefits, and authorization indicators before service.
3. Discover available coverage. Insurance discovery can identify coverage that prevents an account from being classified as self-pay unnecessarily.
4. Secure authorization before care. Prior authorization should surface payer requirements, documentation gaps, pending decisions, and service changes before they cause delays or non-covered balances.
5. Set a reliable expectation. Price transparency and patient estimates should combine benefit information, contracted rates, known services, and clear assumptions. Estimates should be updated when the care plan changes.
6. Screen for appropriate assistance. Financial clearance and counseling should connect eligible patients with financial assistance, charity care, Medicaid screening, or suitable resolution pathways before balances age.
7. Make the record claim-ready. Clinical documentation integrity and health information management support should resolve missing or ambiguous information before coding and billing.
8. Protect coding and charge accuracy. Medical coding, charge capture optimization and revenue integrity should ensure the claim reflects documented care without omissions, duplication, or unsupported charges.
9. Validate the claim and responsibility. Clean-claim validation should stop preventable defects before submission, while payment posting and reconciliation should ensure payer and patient amounts are allocated correctly.
10. Communicate and resolve responsibly. Patient communication and self-pay, charity care, and Medicaid screening should give patients understandable information, accessible help, and a clear route to resolution. HFMA’s 2024 best practices link a good financial experience with lower administrative cost, stronger financial results, and better patient decisions.
A control dashboard makes patient risk and ownership visible. | Make Ownership Visible
Open accountability keeps prevention from becoming another checklist. | Measure Patient Impact
Controls work only when exceptions have an owner, an escalation path, and a feedback loop. Open Accountability makes performance visible without taking control away from the provider. When a corrected statement, denied claim, or changed estimate is traced to its source, teams can remove the failure mode instead of normalizing rework. First-Pass Performance then becomes practical: complete the work correctly at the earliest appropriate step so patients and staff do not repeat it later.
The economic context strengthens the case. The American Hospital Association reported in 2024 that administrative costs exceeded 40% of hospital expenses and that commercial and Medicare Advantage care denials rose 20.2% and 55.7%, respectively, between 2022 and 2023. Downstream appeals remain necessary, but prevention reduces the avoidable touches, delays, and uncertainty that affect both provider finances and patient confidence.
Patient-centered measures show whether the controls are working. | Build Upstream Resilience
Executives should review record-match accuracy, eligibility-related denials, authorization turnaround, estimate accuracy, assistance-screening completion, pre-bill defect interception, clean-claim rate, avoidable patient-balance transfers, corrected statements, inquiry volume, and time to resolution. These measures connect elevating the patient experience with reducing cost to collect and transforming revenue cycle performance.
Providers should review patterns by payer, facility, service line, and control owner. This outsourced coding transition case study shows how visible governance, rapid workflow stabilization, and quality control can protect continuity while improving financial resilience. The same discipline applies to patient affordability: find where harm enters, correct the account, and redesign the control so the defect is less likely to recur.
A patient affordability-centered revenue cycle converts the abstract goal of affordability into ten governable controls. It protects clarity before care, accuracy before billing, and access to help before a balance becomes a crisis. Most importantly, it gives healthcare leaders a practical way to improve patient trust while strengthening first-pass operational and financial performance.

How revenue cycle management makes healthcare more affordable for patients
Healthcare affordability starts before the patient receives a bill. | Affordability Starts Upstream
Revenue Cycle Management (RCM) can support patient affordability by confirming coverage, identifying financial assistance, producing reliable estimates, preventing billing errors, and resolving insurance responsibility before balances reach patients. It does not directly reduce the clinical price of care. It does, however, limit avoidable financial harm created when administrative work is incomplete, inaccurate, or delayed.
That distinction matters. A 2024 KFF analysis estimated that Americans owe at least $220 billion in medical debt; about 14 million adults owe more than $1,000. For healthcare providers, affordability therefore includes not only what care costs, but whether patients receive correct coverage information, understandable estimates, accurate statements, and timely help.
Administrative errors can become patient financial problems. | Errors Become Patient Costs
A patient’s financial journey begins at scheduling, not collections. Incomplete registration can lead to failed eligibility and benefits verification. Missing authorization can delay care or shift uncertainty toward the patient. Documentation gaps, incorrect charges, coding errors, payer edits, and posting mistakes can produce denials or balances that require investigation before anyone can explain what the patient truly owes.
The system cost is substantial. The American Hospital Association reported in 2024 that administrative costs represented more than 40% of hospital expenses, while commercial and Medicare Advantage care denials rose 20.2% and 55.7%, respectively, between 2022 and 2023. Each preventable exception creates rework for staff and uncertainty for patients. Better denials management and appeals matters, but preventing defects earlier is more affordable than repeatedly correcting them downstream.
Eight revenue cycle practices can protect affordability. | Eight Preventive Practices
Healthcare providers can strengthen the patient financial experience through connected controls across the revenue cycle:
- Capture accurate demographics and insurance information through consistent patient access management.
- Verify eligibility, benefits, deductibles, and coordination of benefits before care whenever possible.
- Use prior authorization workflows that surface requirements early and escalate exceptions.
- Provide patient-specific estimates with plain-language explanations of assumptions and uncertainty.
- Screen for financial assistance and appropriate payment pathways before avoidable balances age.
- Strengthen medical coding, clinical documentation integrity and revenue integrity so claims and statements reflect the care delivered.
- Validate patient responsibility before statements are released, then reconcile payments accurately through payment posting.
- Use clear, concise, correct communications aligned with HFMA patient financial communication guidance.
A simple affordability control dashboard makes accountability visible.
Providers should measure what patients experience. | Measure Patient Impact
Traditional revenue cycle measures remain important, but affordability requires a patient-centered scorecard. Leaders should monitor estimate accuracy, eligibility-related denials, authorization-related delays, pre-bill error interception, corrected statements, avoidable patient-balance transfers, inquiry volume, financial-assistance screening, and time to resolution. These indicators connect elevating patient experience with reducing cost to collect and improving revenue integrity.
They also make ownership visible. With Open Accountability, every exception should have a named owner, a defined escalation path, and a feedback loop to the step where the defect began. Technology can support this discipline by connecting EHRs, payers, clearinghouses, and teams through revenue cycle execution systems such as RevAmp and reliable EHR integrations.
First-pass performance turns administrative work into patient trust. | From Rework To Trust
Affordability improves when providers stop treating every error as an isolated downstream task. First-Pass Performance means completing work correctly upstream so patients and staff do not repeatedly revisit the same coverage, authorization, coding, claim, or billing issue. It helps reduce revenue leakage, accelerate cash and protect patients from avoidable confusion at the same time.
The operational lesson is simple: follow the patient balance upstream. A provider that can identify why an inaccurate or unexpected balance was created can redesign the process that produced it. This case study illustrates how a health system used agentic AI eligibility verification to reduce preventable eligibility denials by 26% and saved $3.6 million per month in the process. More broadly, transforming the revenue cycle requires connected workflows, transparent measures, and accountability for outcomes, not only activity.
For executives, the priority is not a collection of disconnected projects. It is a governed operating model that links the front, mid, and back office around a shared view of the patient account. Monthly reviews should examine where estimates changed, why responsibility shifted, which statements were corrected, and whether the originating defect was removed. Teams can then distinguish unavoidable complexity from preventable variation, direct resources toward the highest-impact breakdowns, and verify that automation improves accuracy rather than merely moving work faster. This creates a practical bridge between affordability, operational resilience, and financial sustainability.
Healthcare affordability is larger than revenue cycle management. Yet revenue cycle leaders control many moments that shape whether patients understand, trust, and can act on their financial information. When those moments work correctly the first time, providers reduce rework while giving patients greater clarity before, during, and after care.

Re-Engineering Revenue Cycle for the AI Era
Re-engineering revenue cycle for the AI era.
Artificial intelligence is moving into coding, clinical documentation, authorization, analytics, and other parts of the revenue cycle. But in my work with healthcare leaders, I continue to see the same tension: technology can accelerate a process without correcting the design beneath it.
That tension framed “Back to First Principles: Re-Engineering the Revenue Cycle for the AI Era,” a Vee Healthtek webinar presented in partnership with Becker’s Healthcare. I had the opportunity to moderate a conversation with Dawn Castro of Surgery Partners, Shannan Bolton of Stanford Health Care, and Peter Thompson of UF Health. Together, we explored what revenue cycle leaders must reconsider before scaling AI.
My clearest takeaway was this: AI value begins with redesigning the work. Leaders need to understand why a process exists, where defects originate, how users experience the workflow, and which outcomes the technology is expected to change.
Start with the work, not the technology. | Start With the Work
Revenue cycle improvement often begins with a familiar question: how can we make the current process faster? Shannan challenged that starting point. Before optimizing or automating a workflow, leaders should ask whether the work should exist in its current form and whether the process was designed to prevent problems or manage them after they occur.
“Our first question is not how the work is done today, but why it should exist at all.”
Shannan Bolton, Stanford Health Care
Denial management was a useful example. A workflow designed primarily to recover dollars after a claim fails may become more efficient without reducing the source of the denial. Shannan also noted that a result that remains consistent over time can point to the design, rather than an isolated execution issue. This shifts the conversation from who made an error to what the process repeatedly produces.
Fit AI to operational reality. | Fit AI to Operations
Dawn’s experience reinforced why a promising capability can still miss its expected value. An authorization use case may look attractive at an enterprise level, but performance can vary across service lines, payers, states, systems and user groups.
“What can you actually do today? Let’s focus on those service lines instead of the big, pie-in-the-sky opportunities.”
Dawn Castro, Surgery Partners
Her team’s work showed the importance of observing how people use technology in practice. Seat rides exposed integration gaps, repeated work and the trust issues that develop when users have experienced unreliable tools. The lesson for me is that AI adoption is not a communication task added after implementation. It must be designed into the workflow from the beginning.
Peter shared a related example from clinical documentation integrity. When an initial implementation did not sufficiently reflect clinicians’ day-to-day experience, the organization stepped back and involved clinician work groups in shaping the reimplementation. The technology had to fit the people and the work, not the other way around.
Move prevention upstream. | Move Prevention Upstream
The panel also returned to the need to move attention earlier in the revenue cycle. Recovery work will remain necessary, but leaders should not judge performance only by how effectively teams resolve downstream defects.
“There is a lot that we can do to prevent things from occurring in the first place.”
Peter Thompson, UF Health
Peter described denial-prevention work groups that examine root causes and look for earlier intervention points. This idea connected with the measures discussed across the panel: revenue leakage, first-pass payment, yield, avoidable denials, speed to payment, and the percentage of accounts requiring human intervention. Each offers a different view, but all help leaders see whether redesign is reducing avoidable work or simply moving it faster.
A first-principles sequence for revenue cycle AI.
-
1. Question the work
Ask why the work should exist.
-
2. Diagnose the cause
Separate people, process, and technology issues.
-
3. Redesign the workflow
Move defects upstream and remove low-value steps.
-
4. Introduce technology
Fit the use case to users, service lines, and systems.
-
5. Monitor outcomes
Track adoption, denials, leakage, cash, and intervention.
Redesign roles and oversight. | Redesign Roles and Oversight
AI also changes the work people perform. Peter described a shift from completing tasks to auditing AI-generated output. That shift requires skills in exception management, quality review, and identifying when technology is not performing as expected.
“With AI, we’re moving people from being doers to being auditors.”
Peter Thompson, UF Health
Shannan discussed roles focused on automation leadership, workflow review, and post-launch monitoring. Dawn extended the point to product ownership, RFP discipline, and technology-vendor management. These are not supporting activities around AI. They are part of the operating model required to govern it with open accountability.
Retire low-value work. | Retire Low-Value Work
Re-engineering is also about deciding what to stop. Shannan described efforts to remove duplicate work queues, manual reconciliations, low-value reviews, and overlapping tools. The objective is not consolidation for its own sake. It is to create a less fragmented environment in which teams can act on insights instead of maintaining unnecessary activity.
What I would ask revenue cycle leaders to consider. | Leadership Takeaways
- Does the work still need to exist in its current form?
- Is the AI use case aligned with the users, service lines, payers and systems it will affect?
- Are we preventing avoidable defects or becoming faster at recovering from them?
- Who owns adoption, auditing and performance after the technology goes live?
- Which outcomes will show that the operating model has improved?
The organizations best positioned to scale AI will be those willing to question the work before automating it, involve the people closest to the process, retire unnecessary activity and make performance visible. That is the work behind an AI-ready revenue cycle.

Why approval rates miss the real cost of prior authorization
High prior authorization approval rates can still hide care delays, slower cash, and rising administrative costs. Approval rates reveal little about revenue held in unresolved cases or scheduled capacity affected by payer decisions. Health systems need to manage prior authorization as a revenue-risk workflow tied to cash timing, payer performance, and service-line economics.
Prior authorization in healthcare revenue cycle management is the payer approval process required before selected services qualify for reimbursement. The issue carries added urgency as 2026 comes to a close. Impacted payers are now operating under requirements that generally took effect January 1, 2026, while major API requirements generally take effect in 2027. The current transition gives finance and revenue cycle leaders a limited planning window to establish baseline performance, use newly available payer data, and prepare integrations before electronic exchange expands.
Authorization performance can give finance a false signal. | Authorization Performance Signals
Health systems often evaluate prior authorization through approval rates, productivity, and work-queue volume. These measures show activity, though they provide an incomplete view of financial performance. A case approved after cancellation can count as a successful authorization while the associated revenue moves out of the forecast. An approval obtained after several manual touches can protect reimbursement while increasing cost-to-collect.
A more useful executive view connects authorization status with expected reimbursement and scheduled capacity. Finance and revenue cycle leaders should be able to see:
- Revenue tied to unresolved cases within the next 3, 7, and 14 days
- Expected reimbursement delayed by authorization-related rescheduling
- Authorization labor cost by payer and service line
- Initial denials caused by missing, expired, or mismatched approvals
- Scheduled capacity at risk because payer decisions remain pending
This model exposes the difference between administrative completion and financial conversion. It also gives treasury and finance teams a clearer view of revenue likely to shift between reporting periods.
Payer requirements create a shadow discount on contracted revenue. | Shadow Discount on Revenue
A negotiated rate overstates payer value when the health system must absorb repeated follow-up, clinical escalation, rescheduling, or appeal costs before receiving payment. Payer-specific authorization friction creates a shadow discount on contracted revenue because administrative cost and cash delay reduce the economic value of the agreed rate.
Two payers may reimburse the same amount for an outpatient procedure while producing different margins. One may accept a consistent documentation set and issue timely decisions. Another may require additional records, route cases through clinical review, and generate more post-service disputes. Equal contracted rates can therefore produce unequal net revenue.
Payer scorecards should extend beyond reimbursement rates and denial percentages. Useful comparisons include:
- Authorization touch count and labor minutes per request
- Median decision time by service category
- Approval timing relative to the scheduled service date
- Appeal overturn rate
- Authorization-related reschedule and cancellation value
- Cost-to-collect after administrative effort
Impacted payers must publish prior authorization measures from the previous calendar year, including approval and denial rates, appeal outcomes, and response times. They must also publish a clear list of medical items and services requiring prior authorization, excluding drugs.
Public payer metrics offer a benchmark, while internal data shows the true cost of delays, denials, and rework. Health systems can use both sources to strengthen payer negotiations and assess how authorization requirements affect contract economics.
The 2026 rules create an operating deadline, while 2027 creates a technology decision. | 2026 and 2027 Deadlines
Medicare Advantage and affected Medicaid and CHIP payers generally have 72 hours for expedited requests and seven calendar days for standard requests. These timeframes apply to covered medical items and services, excluding drugs.
Faster payer decisions improve only the portion of the cycle after the payer receives a complete request. Internal delays can consume several days while teams collect clinical documentation, resolve eligibility questions, or identify the correct submission process. The health system can still experience a long authorization cycle even when the payer meets its deadline.
CMS places the 2027 API requirements on impacted payers. Health systems must decide how to integrate the new connections into authorization workflows. Current EHR, clearinghouse, and workflow technology must be able to use the data without creating another disconnected queue.
A practical 2026 readiness plan should address:
- Current authorization cycle time before payer submission
- Payer and service categories covered by the rule
- Drug authorizations and commercial plans outside the rule’s scope
- EHR and workflow integration requirements
- Expected labor reduction and implementation cost
- Ownership of API data quality and exception handling
The business case should measure more than staff hours saved. It should estimate cash acceleration, avoided reschedules, denial reduction, and capacity protected by earlier decisions.
Prior authorization exposure should enter cash forecasting. | Authorization-Weighted Cash Forecasting
Authorization work frequently sits outside the data used for short-term cash forecasting. This separation leaves finance teams unable to distinguish scheduled revenue likely to proceed from revenue dependent on unresolved payer approval.
A revenue-weighted authorization forecast can close this gap. Each scheduled case can receive an exposure value based on:
- Expected net reimbursement
- Time remaining before the service date
- Documentation readiness
- Historical payer response time
- Financial effect of rescheduling or cancellation
Finance teams can then segment scheduled revenue by authorization status. Approved cases carry greater payment certainty. Exposed cases require intervention before the service date, while delayed cases may shift into a later forecast period.
The same analysis can quantify A/R risk. A service performed with an invalid authorization may enter billing on time while carrying a higher probability of denial, appeal, or write-off. Flagging this exposure before service creates an opportunity to prevent the receivable rather than manage it after the claim fails.
Service-line growth requires authorization economics. | Service-Line Authorization Economics
Prior authorization can influence whether increased demand produces profitable growth. A health system may recruit specialists, add procedural capacity, or expand an infusion program while underestimating the authorization infrastructure needed to support higher volume. Scheduled demand can rise while collectible revenue trails because approvals miss treatment dates or require labor beyond the original business case.
Growth models should include the percentage of projected volume requiring authorization, expected approval lead time, and payer mix. They should also account for staff capacity, clinical escalation requirements, and the direct cost of unused procedural capacity.
This analysis helps leadership answer a more consequential question: Can the revenue cycle support the planned service volume at the assumed margin? If authorization readiness cannot scale with demand, the expansion plan requires workflow investment before additional clinical capacity comes online.
Update workflows to prevent avoidable rework and build revenue resilience. | Workflow and Revenue Resilience
Preventing avoidable rework requires earlier identification of payer requirements and clearer escalation paths. Authorization screening should begin as close to the scheduling or ordering decision as available information allows. Cases with high reimbursement value, short lead times, or complex clinical criteria should enter prioritized queues instead of moving through standard first-in, first-out processing.
Workflow rules should define when a case needs clinical documentation, peer-to-peer review, or financial clearance. Leaders should also assign responsibility for payer-rule maintenance and monitor whether updates reach schedulers, patient access teams, and authorization specialists before outdated requirements generate denials.
A financially aligned scorecard should track:
- Pre-service resolution rate
- Revenue-weighted approval timeliness
- Revenue exposed within scheduled service windows
- Authorization-related initial denial rate
- Avoidable reschedule value
- Cost per resolved authorization
Together, these measures reveal whether the organization protects reimbursement before service, controls administrative cost, and supports operational continuity.
How Vee Healthtek supports prior authorization performance. | How Vee Healthtek Helps
Vee Healthtek combines practitioner-led revenue cycle expertise, AI-enabled workflows, and global delivery to strengthen prior authorization performance. Teams connect payer requirements, clinical documentation, and service-date risk to identify high-priority cases earlier and move them through the right escalation path before delays affect care or reimbursement.
AI-enabled workflows monitor changing payer rules, surface missing information, and prioritize work by financial and operational risk. This earlier intervention reduces avoidable rework caused by incomplete submissions, repeated payer follow-up, documentation retrieval, rescheduling, and appeals. Clear governance and visible performance measures help organizations manage authorization volume consistently across payers, facilities, and service lines.
Stronger First-Pass Performance means fewer avoidable delays and denials and less administrative effort spent correcting preventable issues. Earlier visibility into revenue and scheduled capacity at risk helps leaders protect reimbursement, control cost-to-collect, and create a more predictable path from scheduled care to payment.
Key Takeaways
- Approval rates can mask revenue delays, excess labor, and lost scheduled capacity.
- Public payer metrics create a new opportunity to quantify authorization friction during payer negotiations.
- The 2026 operating requirements and 2027 API deadline require coordinated revenue cycle, finance, and technology planning.
- Revenue-weighted authorization reporting can strengthen cash forecasts and expose service-line risk earlier.
- Authorization capacity should enter growth planning before clinical volume expands.

Contracted rate vs. realized reimbursement
A higher contracted rate can still produce a lower return. Payers can change reimbursement economics through tighter prior authorization rules, narrower medical necessity criteria, expanded coding edits, and additional documentation requirements. These policies give payers greater influence over utilization and claim expense without reopening contracts. Providers retain the negotiated rate on paper while absorbing more denials, longer payment cycles, and greater collection effort.
Realized reimbursement is the amount a healthcare organization ultimately collects after payer policies and claim requirements affect the contracted amount. Negotiated rates measure pricing, while realized reimbursement measures how effectively expected revenue becomes cash. Protecting healthcare financial performance requires claim-level visibility into payment loss, payment delays, and the administrative cost of collection.
How payer policies reduce the effective value of provider contracted rates. | Contracted Rates Versus Returns
A contracted rate applies only when a claim satisfies every payment condition. Each new payer requirement creates another point where reimbursement can decrease or stall. The combined effect can function like a shadow discount for the provider: the published rate remains unchanged while denials, partial payments, delayed cash, and recovery expenses reduce its effective value.
A health system can negotiate a rate increase and realize little margin improvement. Consider a service line with $50 million in annual allowed reimbursement. A 4% increase appears to add $2 million. If policy changes contribute to a 2% decline in payment realization and $750,000 in incremental collection expense, more than half of the expected value disappears before accounting for delayed cash. This illustrative example shows why rate schedules alone provide an incomplete view of payer economics. Here are five actions CFOs can take to identify this exposure and protect reimbursement.
1. Measure net reimbursement yield. | Measurenet Reimbursement Yield
Realized reimbursement rate offers a useful starting point:
Realized reimbursement rate = Net payment collected ÷ Expected allowed reimbursement
Organizations should calculate this measure by payer, plan, service line, procedure, and facility. A payer may perform well in aggregate while producing material losses across a narrow group of high-value services.
A second measure adds the cost required to secure payment:
Net reimbursement yield = (Cash collected − incremental collection expense) ÷ Expected allowed reimbursement
Collection expense may include authorization corrections, clinical record retrieval, coding reviews, appeals, and A/R follow-up. Two payers may eventually reimburse the same amount, while one requires substantially more intervention and holds cash longer. Net reimbursement yield exposes the difference in margin contribution.
Leaders should separate reimbursement erosion into three categories:
- Payment loss: Denials, downgrades, and unresolved underpayments
- Payment delay: Claim pends, record requests, and extended reviews
- Collection expense: Corrections, appeals, and follow-up activity
This distinction shows whether the organization needs to prevent revenue leakage, accelerate cash, or reduce cost-to-collect.
2. Identify the policies creating the largest economic discount. | Find Policy-Driven Discounts
Monthly denial totals show where claims failed, although they may obscure the payer policy driving the failures. Revenue cycle leaders should connect denials, underpayments, and payment delays to specific policy changes and effective dates.
Start with payers and service lines where contracted rates improved while payment realization, collection time, or denial performance worsened. This contradiction can reveal policy-driven erosion inside an apparently favorable agreement.
A payer policy impact scorecard should capture:
- Affected payer, plan, service, and claim population
- Expected reimbursement exposure
- Likely effect on payment timing
- Incremental collection effort
- Workflow requiring an update
- Implementation owner and validation date
Leaders can prioritize each change using a basic exposure calculation:
Financial exposure = Affected claim volume × Expected reimbursement variance × Probability of nonrecovery
This approach directs resources toward material risks rather than treating every policy bulletin with equal urgency.
3. Connect each policy to the earliest preventable failure. | Prevent Failures Earlier
Payer policies often reach revenue cycle functions as separate operational updates. Patient access receives a new authorization rule. Utilization review sees revised medical necessity criteria. Coding encounters a new edit after services have already occurred.
A policy-impact review should identify where the organization can reliably prevent the failure. For example, a payer may require additional clinical evidence for an imaging procedure. Updating the authorization workflow alone may leave exposure if the medical record lacks the required evidence. Scheduling must identify affected appointments, clinicians need relevant documentation guidance, and utilization review must validate medical necessity before billing.
Teams should answer four questions for each material change:
- Which claims and services fall within scope?
- Which workflow contains the earliest intervention point?
- Which accounts already in progress carry exposure?
- Which performance measure will validate the response?
This process moves denial prevention upstream and protects first-pass yield. It also prevents staff from discovering new requirements after claims enter A/R.
4. Incorporate payer behavior into forecasts and governance. | Improve Forecasts and Governance
Cash forecasts based primarily on contracted rates can overstate expected collections when payer policies lower payment probability or extend processing time. Finance teams should apply payer-specific realization and timing factors to expected reimbursement.
Forecast assumptions might reflect:
- Historical payment realization for affected claim cohorts
- Average time from initial submission to final payment
- Appeal success rates and recovery time
- Policy-related denial and underpayment trends
These factors help finance distinguish temporary execution issues from a structural change in payer economics. They can also improve denial reserves, service-line margin analysis, and near-term cash projections.
Revenue cycle governance should assign clear ownership for policy intake, interpretation, implementation, validation, and escalation. Each material change needs an effective date, financial exposure estimate, accountable owner, and expected outcome.
Monthly payer performance reviews should address five questions:
- Where is the gap between expected and realized reimbursement growing?
- Which policies created the greatest cash or margin exposure?
- Where did requirements fail to reach workflows before the effective date?
- How much collection effort did the organization expend?
- Which trends require payer escalation or contract action?
5. Update workflows before policy changes become denials. | Update Workflows Proactively
Large-scale transformation is rarely the first requirement. Most organizations need a faster process for inserting new payer requirements into existing workflows. An authorization prompt during scheduling, updated documentation guidance at the point of care, or a payer-specific prebill edit can prevent a policy change from becoming a denial.
Workflow updates should occur at the earliest reliable intervention point. A billing edit may catch an issue before submission, although it may arrive too late to correct missing clinical evidence. Earlier controls protect reimbursement and reduce the labor required for claim correction, appeal preparation, and follow-up.
Leaders should measure whether each update produces a financial result:
- Avoided denial value
- Improvement in first-pass yield
- Change in A/R days
- Reduction in account touches
- Net effect on cost-to-collect
Centralizing payer requirements also supports operational continuity. Governed rules reduce dependence on individual knowledge and local spreadsheets. Faster policy implementation limits leakage, prevents avoidable rework, and strengthens revenue resilience across facilities and service lines.
How Vee Healthtek helps protect realized reimbursement. | Protect Realized Reimbursement
Payer policy intelligence creates value only when it changes how teams work before a claim fails. Vee Healthtek helps healthcare organizations build a direct path from policy identification to financial action. Revenue cycle specialists assess which claims carry exposure, identify the earliest workflow where teams can prevent payment loss, and implement the required update across patient access, utilization review, coding, billing, denial management, underpayment recovery, or A/R follow-up.
The approach focuses on three outcomes:
- Detect reimbursement risk earlier: AI-enabled analysis identifies emerging payment variance and prioritizes affected claims by financial exposure.
- Act before revenue enters extended A/R: Payer requirements move into existing work queues, documentation guidance, claim edits, and escalation processes at the earliest reliable intervention point.
- Measure the economic result: Performance tracking connects workflow updates to net reimbursement yield, first-pass yield, denial reduction, cash acceleration, and cost-to-collect.
Vee Healthtek combines revenue cycle expertise, practitioner insight, workflow design, and a global delivery architecture to support consistent execution across payers, facilities, and service lines. This structure helps organizations respond to policy changes without relying on disconnected spreadsheets, individual knowledge, or recovery work after claims have already failed.
The result is a more accountable approach to reducing preventable denials, improving financial predictability, and building revenue resilience as payer requirements continue to change.
Key takeaways
- Contracted rates can overstate the economic value of a payer relationship.
- Payer policies can reduce effective reimbursement through payment loss, delay, and collection expense.
- Net reimbursement yield reveals the margin impact hidden by traditional rate analysis.
- Policy impact should influence forecasts, workflow priorities, and payer negotiations.
- Timely workflow updates prevent avoidable rework and strengthen revenue resilience.

Where revenue cycle leaders should scale AI for ROI
Revenue cycle AI has reached a portfolio decision point.
For Heads of Revenue Cycle, the question is no longer whether Artificial Intelligence (AI) belongs in Revenue Cycle Management (RCM). It is where AI should move from experiment to scaled execution. Bessemer Venture Partners and Bain & Company’s 2026 Healthcare AI ROI Scorecard reports 4.0x realized ROI for provider revenue cycle AI and says 67% of provider RCM respondents run semi-autonomous or fully autonomous agents. Those category-level findings are a signal, not a blanket business case: each workflow must still earn its place in the portfolio.
Adoption and ROI create a practical revenue cycle AI roadmap. | Read The ROI Map
The report’s ROI Scorecard plots overall adoption horizontally and realized ROI vertically. For revenue cycle leaders, four portfolio positions translate into practical choices: scale high-adoption, high-return workflows; validate low-adoption, high-return opportunities; redesign adopted workflows with weaker returns; and monitor immature use cases. This view is more useful than counting pilots because it connects deployment maturity to value already realized.
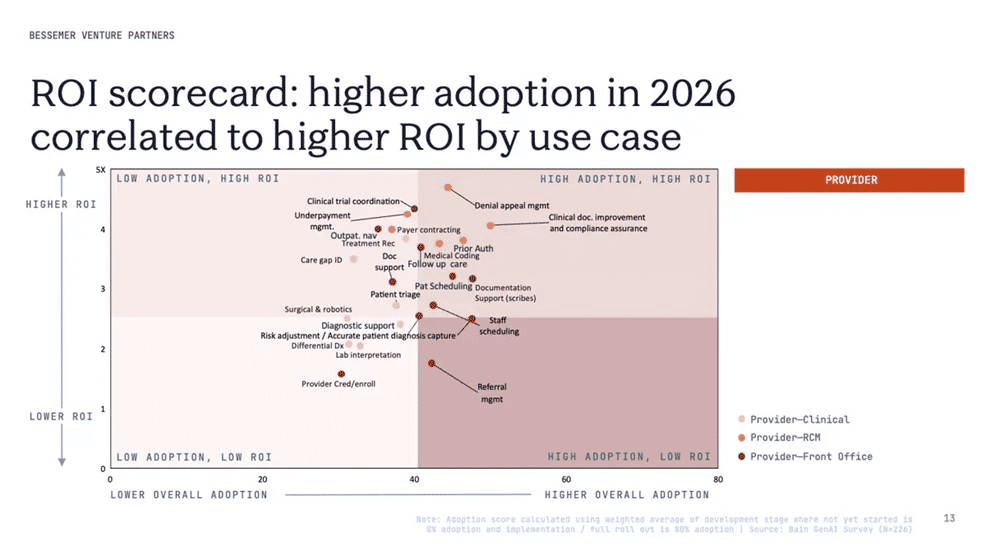
Figure 1. Provider AI use cases mapped by adoption and realized ROI.
Source: Bessemer Venture Partners and Bain & Company, The 2026 Healthcare AI ROI Scorecard; Bain GenAI Survey, N=226.
Scale the revenue cycle workflows already combining adoption and return. | Scale Proven Workflows
Denials should become a prevention system, not a faster appeal queue.
Denial and appeal management is a scale-ready workflow with measurable potential. HFMA reported in 2026 that about one in five providers applied AI to denials management, showing that strong potential does not equal universal maturity. Leaders should use AI to prioritize work and assemble evidence, then feed denial intelligence upstream into eligibility and benefits verification, prior authorization and clean-claim controls. Otherwise, AI merely accelerates rework.
CDI and coding need accuracy before autonomy.
Clinical documentation improvement and compliance assurance, prior authorization and medical coding are also strong candidates for selective scale. AHIMA noted in 2024 that weak documentation and coding quality can drag down AI performance. Scale should therefore pair clinical documentation integrity with medical coding, audit controls and expert validation. The goal is not touchless work at any cost. It is defensible first-pass performance that reduces corrections after submission.
Validate high-return opportunities before the industry normalizes them. | Validate Emerging Opportunities
Underpayment management combines promising returns with room for wider adoption. That makes underpayment recovery and payer variance resolution a candidate for controlled validation: establish a baseline, define recoverable variance, account for implementation cost and test whether detection converts into cash. Likewise, leaders should connect revenue integrity and leakage prevention to contract intelligence and payment outcomes rather than treating alerts as value.
Investigate adopted workflows that are not returning enough.
Patient scheduling and referral management require a sharper outcome definition. That does not make either workflow unimportant. It means leaders should sharpen the outcome definition. For scheduling and registration, is AI improving completed appointments, registration quality or staff capacity? For patient access management, is automation preventing downstream denials or simply moving more tasks? Adoption without an explicit financial and operational path can make a busy workflow look successful while the revenue cycle still cleans up its defects.
Build an AI portfolio instead of collecting disconnected tools. | Build The AI Portfolio
The American Hospital Association reported in 2024 that 46% of hospitals and health systems used AI in RCM and 74% used some form of revenue cycle automation. The harder question is: which investments can scale into governed execution? Connect claims editing and clean-claim validation, accounts receivable follow-up and payment posting and reconciliation through shared data, priorities and outcome measures. Revenue cycle platforms should be judged by whether intelligence becomes action, experts receive the right exceptions and leaders can see what changed.
Use this executive dashboard to decide what scales next. | Use The Decision Dashboard
The following framework converts adoption and ROI into four decisions.
Open accountability turns AI activity into durable performance.
Before scaling, ask five questions: What measurable problem is being solved? What baseline defines realized improvement? What can AI execute without intervention? Which exceptions require expert judgment? Can every action, error and outcome be traced? Those questions align AI investment with First-Pass Performance and Open Accountability. They also prevent technology from hiding fragmented ownership. The strongest portfolio does more than recover revenue faster. It learns from downstream failures, corrects upstream causes and gives the provider visibility and control.
The next revenue cycle AI advantage will come from selective scale.
Every revenue cycle AI use case does not scale equally. The framework helps leaders distinguish proven workflows, under-adopted opportunities and applications that need redesign. A practical next step is to assess each use case against financial value, rework reduction, execution readiness, autonomy potential and governability. That is how health systems move from isolated pilots to scaling with technology, reducing cost to collect and accelerating cash. This physician enterprise case study illustrates the value of treating revenue cycle as a learning system rather than a sequence of disconnected queues.

How healthcare providers can prove 3x ROI from AI in revenue cycle
AI now has to earn its place in the revenue cycle. | The 3x Test
Healthcare AI has moved from experimentation to financial scrutiny. A 2026 Bain and KLAS healthcare IT study of 303 U.S. healthcare executives found that about 95% of providers and payers place software and digital technology among their top five priorities. Yet leaders increasingly want a specific use case, measurable returns, and short time to value. Among organizations with formal thresholds, the most common hurdle is a 3.0x to 3.9x return.
That changes the question for a healthcare leader. The decision is no longer whether AI sounds promising. It is whether an AI-enabled workflow can improve cash, cost, capacity, or risk enough to justify its full economic footprint, while strengthening the patient and workforce experience.
The 3x test begins with a financial baseline, not a demo.
A credible business case starts with the current cost of the problem. Measure denial write-offs, avoidable touches, manual minutes, outsourced expense, delayed billing, underpayments, and the opportunity cost of staff trapped in queues. Then establish the baseline across front-office workflows, mid-office workflows, and back-office operations before the AI intervention.
Use a simple formula: annual value equals incremental revenue protected or recovered, plus operating cost removed, plus the financial value of capacity created, minus technology, integration, implementation, governance, and change costs. A 3x case exists when annualized measurable value is at least three times the fully loaded investment, using conservative assumptions and an agreed measurement window.
Four value pools reveal whether AI is creating enterprise value. | Value Pools
First, quantify revenue outcomes. AI may support faster cash conversion, identify revenue leakage, or improve claim quality. Second, measure labor economics through lower cost to collect, fewer repeat touches, and better exception routing. Third, value capacity created: staff time redirected from repetitive work to complex accounts, payer escalation, or patient support. Fourth, measure speed: shorter authorization, coding, billing, denial, and A/R cycle times.
The American Hospital Association reported that hospital use of predictive AI integrated with EHRs rose from 66% in 2023 to 71% in 2024, with administrative-efficiency use cases growing fastest. AHIMA likewise describes AI and machine learning as tools that can modernize billing and coding. Adoption, however, is not ROI. Financial value appears only when insight changes the work and the outcome.
Detection creates potential, but execution converts it into return. | Execution Over Detection
An algorithm can flag a denial risk, missing documentation, coding variance, or authorization gap. If the alert enters another queue, arrives after the claim is built, or lacks an accountable owner, the organization has purchased detection without resolution. Rework remains, and the apparent productivity gain may simply move labor downstream.
The stronger design connects intelligence to action. In medical coding, that means pairing automation with certified judgment and quality controls. In scheduling and registration, it means correcting defects before they contaminate eligibility, authorization, claims, and collections. Across revenue cycle technology, it means integrating AI with workflows, escalation rules, audit trails, and human exception management.
This is why first-pass performance is a better north star than automation volume. Measure the percentage of work completed accurately the first time, then trace repeat defects to their source. A stronger first pass reduces corrections, handoffs, delays, and rescues while improving the reliability of financial results.
An executive dashboard keeps the 3x claim honest. | The Executive Dashboard
The dashboard should show baseline, target, actual result, variance, financial value, owner, and next corrective action. It should distinguish gross benefits from validated savings, isolate one-time implementation costs, and prevent double counting across revenue, productivity, and capacity. A co-managed operating model can add capacity, but the provider should retain visibility into assumptions, work queues, quality, and realized outcomes.
Open accountability turns ROI from a forecast into a discipline. | Scaling With Accountability
AI ROI compounds when leaders can see what changed, why it changed, who owns the result, and what will happen next. Open Accountability creates that operating discipline without asking the healthcare provider to surrender control. Shared measures and transparent escalation expose weak signals early, while root-cause learning prevents the same breakdown from recurring.
Before scaling, require evidence at the workflow level: sustained first-pass improvement, lower rework, validated financial impact, stable quality, and acceptable compliance and patient risk. Then scale with technology across comparable workflows, rather than applying one enterprise-wide assumption to every function. The goal is not more AI. It is a transformed revenue cycle in which AI, automation, and practitioners consistently convert earned revenue into predictable performance. This Vee Healthtek case study on reducing A/R illustrates the value of combining operational learning with measurable financial improvement.
Have a Question for Vee Healthtek?
Vee Healthtek is a practitioner-led, technology-powered revenue cycle partner focused on building resilience through first-pass performance and open accountability. For service inquiries, company information, or questions about our latest announcements, complete the form below. We’ll direct your interest to the right team.
Continue exploring expert perspectives, industry trends, and practical strategies for improving revenue cycle performance.
Explore Points Of View